Tixel 2
Tixel 2 is available at Rose Optometry, Hamilton. This page explains what it is, who it suits and how to be assessed for it.
Questions about Tixel 2 are answered by Jacqueline Rowe. Please email Info@roseoptom.co.nz and mark your message for Jacqueline. That reaches her directly and gets you a clinical answer, rather than a general one from our reception team.
Book a Dry Eye Evaluation online: Treatment starts with an assessment. open our online booking — the Dry Eye Evaluation is preselected; just choose a time. This is a paid, in-depth assessment (TearCheck, meibography and ScoutPro osmolarity) and the fee is confirmed when you book. Prefer to talk? Call (07) 847 3195.
What Tixel is
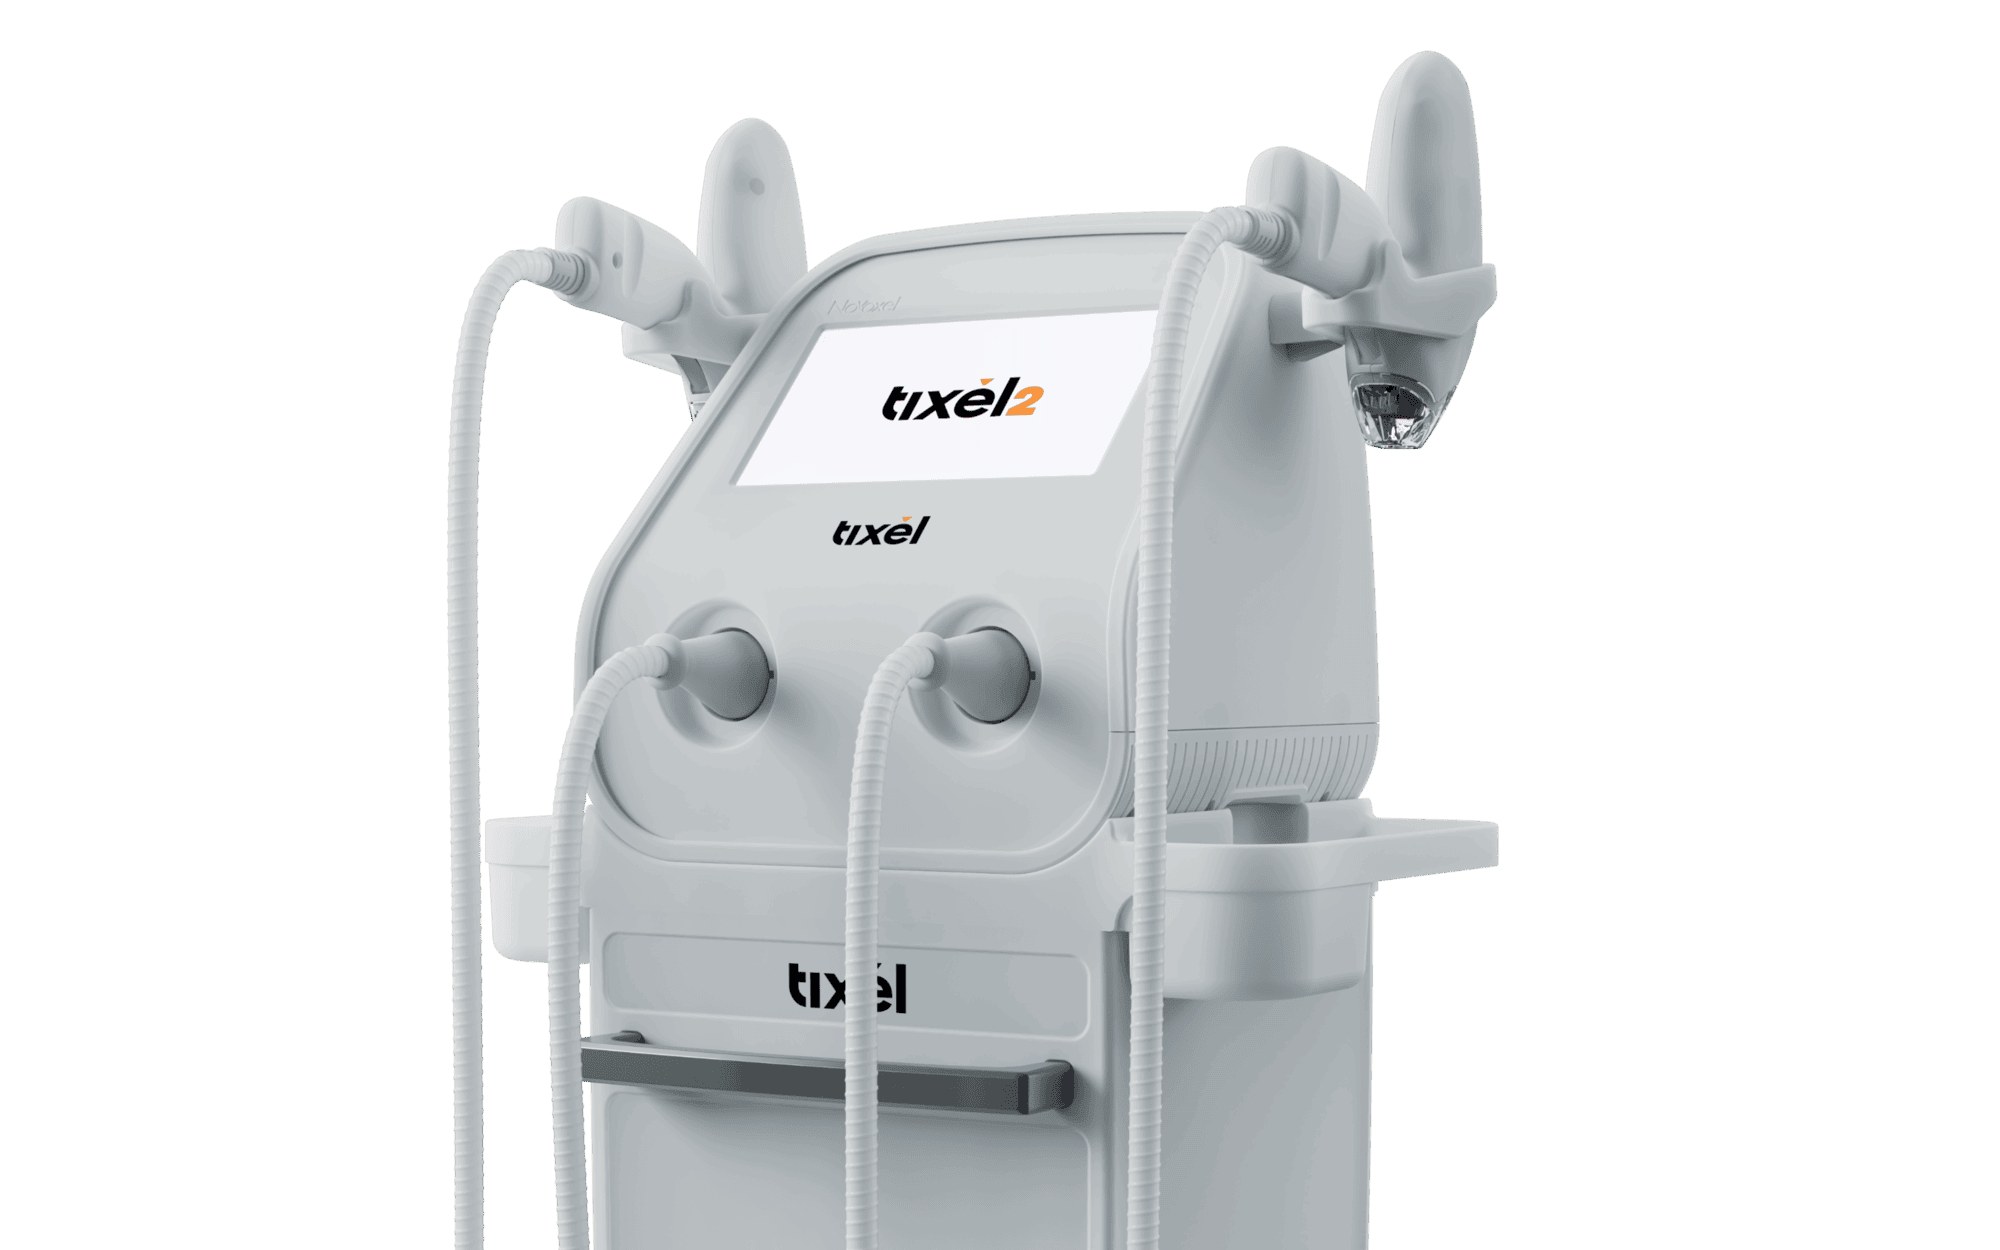
Tixel is a thermomechanical device. A small titanium tip, made up of a grid of tiny pyramids, is heated to a controlled temperature and touched to the skin for milliseconds at a time. The brief contact transfers heat into the very top layers of skin, creating microscopic channels and stimulating the tissue underneath, without cutting, without needles and without laser or light energy. Because there is no light involved, skin type matters less than it does with IPL (dermatology reports include skin types II to V) and it has been applied to periorbital skin and eyelids in published studies.
Two reasons to be interested
1. Dry eye and meibomian gland dysfunction
Applied along the eyelids, Tixel warms the lids and the meibum inside the glands, and appears to improve the quality of the lid tissue around the gland openings so that oil flows more freely. A pilot study and a randomised comparison against LipiFlow report improved tear break-up time, gland function and symptoms in MGD over about three months, and it is being used in Auckland and overseas alongside IPL and LipiFlow, particularly for patients whose skin type or medications rule out IPL. Our article on meibomian gland dysfunction explains why gland function is the heart of most dry eye.
2. Eyelid and under-eye skin
The same controlled heat is thought to stimulate collagen remodelling in the delicate periocular skin. Tixel has been studied for periorbital fine lines, where a randomised comparison found it performed similarly to a non-ablative fractional laser, and it is used for crepey upper-eyelid skin and mild lower-lid laxity. Downtime is typically a day or two of redness rather than the peeling and recovery of ablative resurfacing. It is a treatment for people who want to look rested rather than different, and it sits naturally with an optometrist because we look after the eye behind the eyelid: we assess the tear film, the lids and the ocular surface first, and treat the skin with the eye's health in mind.
Why Hamiltonians no longer need to travel to Auckland
Tixel has until recently only been available in a small number of Auckland clinics. We regularly heard from Waikato patients who had made that trip, sometimes several times for a course. Having it in Frankton means people from Hamilton, Cambridge, Te Awamutu, Morrinsville, Huntly and Raglan can have assessment, treatment and follow-up in one place, alongside the IPL, LipiFlow, Blephasteam and BlephEx already available here.
The evidence, honestly
Tixel has a younger evidence base than IPL or LipiFlow. The dry-eye studies to date are small, mostly short-term (weeks to months) and include one open-label pilot and one randomised comparison against LipiFlow rather than sham; larger, longer controlled trials are still needed. The results so far are promising, and the periorbital aesthetic use has published dermatology studies behind it, but we will describe it as promising rather than proven, and we will not quote outcome figures we cannot back with your own measurements. As with all our dry-eye work, TearCheck, meibography and ScoutPro osmolarity before and after will show whether it is helping you.
What a course looks like
Based on the published protocols, a course is typically around three sessions, spaced a few weeks apart, each taking roughly 20 to 30 minutes with numbing cream beforehand. Suitability is decided at an assessment at our Dry Eye Clinic in Hamilton, because the assessment decides the treatment: for some people IPL, LipiFlow or a Demodex programme will still be the right first step, and for some a combination will make sense. Home care from our online store continues in the background. Assessment is also offered at our affiliated practice, Visique Rototuna Optometrists.
Enquiries and booking
Tixel 2 is available at Rose Optometry. Treatment always begins with a Dry Eye Evaluation, because the assessment decides whether Tixel, another treatment, or a combination is right for you.
For specific questions about Tixel 2, email Info@roseoptom.co.nz marked for the attention of Jacqueline Rowe. Jacqueline handles these enquiries personally. Please email rather than asking at reception — our front desk team are not able to answer detailed clinical questions about this treatment, and emailing means your question reaches the right person first time.
Optometrists for Tixel 2 at Rose Optometry
You will be seen by one of seven therapeutically qualified optometrists — all University of Auckland graduates, all able to prescribe eye medication where it is needed, and all of whom examine patients from six weeks of age.
- Jagrut Lallu — Partner Optometrist · BOptom (Hons), MSc Specialty Lenses (Hons), FIAOMC. Assesses dry eye and eyelid disease and refers within the practice for Tixel 2; Tixel 2 is one of Jagrut's special interests. All special interests: children's vision, myopia management, orthokeratology, keratoconus and scleral lenses, dry eye.
- Jacqueline Rowe — Partner Optometrist · BSc, BOptom. Assesses dry eye and eyelid disease and refers within the practice for Tixel 2; Tixel 2 is one of Jacqueline's special interests. All special interests: dry eye and meibomian gland dysfunction, orthokeratology, keratoconus, children's vision.
- Emilie Lawson — BOptom (Hons) · Accredited Glaucoma Prescriber · ACO Certificate in Advanced Contact Lenses. Assesses dry eye and eyelid disease and refers within the practice for Tixel 2; Tixel 2 is one of Emilie's special interests. All special interests: children's vision, myopia management, orthokeratology, glaucoma, keratoconus, dry eye.
- Jason Shen — BOptom (Hons). Assesses dry eye and eyelid disease and refers within the practice for Tixel 2. Special interests: keratoconus and specialty contact lenses, children's vision.
- Jessica Wood — BOptom (Hons) · Clinical Research Optometrist, New Zealand Eye Research Centre. Assesses dry eye and eyelid disease and refers within the practice for Tixel 2; Tixel 2 is one of Jessica's special interests. All special interests: orthokeratology, keratoconus, dry eye, children's vision, clinical research.
- Stella Wong — BOptom (Hons). Assesses dry eye and eyelid disease and refers within the practice for Tixel 2; Tixel 2 is one of Stella's special interests. All special interests: myopia management, orthokeratology, keratoconus and specialty contact lenses, binocular vision, dry eye, children's vision.
- Anjali Hira — BOptom (Hons). Assesses dry eye and eyelid disease and refers within the practice for Tixel 2; Tixel 2 is one of Anjali's special interests. All special interests: children's vision, orthokeratology, keratoconus, dry eye.
Tixel 2 treatment itself is provided by Jagrut Lallu.
Frequently asked questions
Is Tixel painful?
Numbing cream is used and most people describe a brief hot prickle. Redness and mild swelling settle over a day or two.
Is it a laser?
No. It uses direct, momentary contact heat with no light energy, which is why it has been used on eyelid skin and across a wider range of skin types.
Can I book Tixel now?
Yes. Book a Dry Eye Evaluation and you will be assessed for suitability at that appointment. If you have questions before booking, email Info@roseoptom.co.nz marked for Jacqueline Rowe.
How much does Tixel cost in Hamilton?
We do not publish a figure, because the number of sessions depends on what your assessment shows. Costs are confirmed with you after the Dry Eye Evaluation, before any treatment is booked. For a specific quote, email Info@roseoptom.co.nz marked for Jacqueline Rowe.
Does Tixel work for dry eye?
The early studies, including a randomised comparison against LipiFlow, report improved gland function and symptoms in meibomian gland dysfunction over about three months. The evidence is promising but younger and smaller than for IPL or LipiFlow, which is why we describe it that way and will measure your results.
Is Tixel good for under-eye wrinkles and eyelid skin?
Published dermatology studies report improvement in periorbital fine lines comparable to a non-ablative fractional laser, with a day or two of redness. Results are gradual and natural rather than dramatic. Ask about the aesthetic side at your assessment, or email Jacqueline.
Is Tixel safe near the eyes?
It has been applied to eyelid skin in published studies with protective eye shields in place, and because there is no light energy it does not carry IPL's skin-type restrictions. Suitability is always decided at assessment.
What it costs
Tixel — $1,150 for the course.
Where this treatment is offered to you, the fee is $1,150 for the course.
A Dry Eye Evaluation ($247) comes first, so the treatment is chosen from measurements rather than from symptoms alone.
Questions we are asked about Tixel
What does Tixel do for dry eye?
It applies controlled thermomechanical energy to the eyelid skin, stimulating tissue remodelling around the glands. It is aimed at the lid tissue itself rather than at clearing a blockage, which is why it is sometimes used alongside a treatment that addresses obstruction directly.
Is there downtime?
Mild redness or a warm, slightly sandpapery feeling to the lid skin for a short period afterwards is typical. Most people carry on with their day. We will go through aftercare and sun protection with you.
Is this the same Tixel used for skin treatments?
The technology is the same family, applied with different settings and a different clinical purpose. Here it is used for the eyelids as part of dry eye management, by optometrists, with the eye protected throughout.
Book in Hamilton
Start with a Dry Eye Evaluation. If Tixel is appropriate we will explain why, and if it is not we will say so.
Rose Optometry, 38 Lake Road, Frankton, Hamilton. 07 847 3195. Specific Tixel questions: Info@roseoptom.co.nz, marked for Jacqueline Rowe.
References
- Safir M, Hecht I, Ahimor A, et al. The effect of thermo-mechanical device (Tixel) treatment on evaporative dry eye disease - A pilot prospective clinical trial. Cont Lens Anterior Eye. 2022;45(6):101741. PMID 35864019. doi:10.1016/j.clae.2022.101741
- Sadri E, Verachtert A, Parkhurst GD, et al. Effectiveness and safety of a thermo-mechanical action device versus thermal pulsation device in the treatment of meibomian gland dysfunction. J Cataract Refract Surg. 2025;51(4):274-281. PMID 39680541. doi:10.1097/j.jcrs.0000000000001602
- Sadri E, Verachtert A, Parkhurst GD, et al. Durability of Treatment with a Thermomechanical Device in Meibomian Gland Dysfunction: An Observational Extension Study. J Ocul Pharmacol Ther. 2025;41(5):237-243. PMID 40238710. doi:10.1089/jop.2025.0033
- Salameh F, Daniely D, Kauvar A, Carasso RL, Mehrabi JN, Artzi O. Treatment of periorbital wrinkles using thermo-mechanical fractional injury therapy versus fractional non-ablative 1565 nm laser: A comparative prospective, randomized, double-arm, controlled study. Lasers Surg Med. 2022;54(1):46-53. PMID 34787919. doi:10.1002/lsm.23494
- Wang JV, Bajaj S, Orbuch D, et al. Safety and Efficacy of a Thermomechanical Fractional Injury Device for Periorbital Rhytides. Dermatol Surg. 2023;49(4):374-377. PMID 36826343. doi:10.1097/DSS.0000000000003728
- Daniely D, Judodihardjo H, Rajpar SF, et al. Thermo-Mechanical Fractional Injury Therapy for Facial Skin Rejuvenation in Skin Types II to V: A Retrospective Double-Center Chart Review. Lasers Surg Med. 2021;53(9):1152-1157. PMID 33783848. doi:10.1002/lsm.23400
- Jones L, Craig JP, Markoulli M, et al. TFOS DEWS III: Management and Therapy. Am J Ophthalmol. 2025;279:289-386. PMID 40467022. doi:10.1016/j.ajo.2025.05.039
Frequently asked questions
At Rose, a standard adult eye examination is $129. A new patient appointment takes 45 minutes, and imaging and a full pre-examination workup are included in that price rather than added afterwards. Children and school students are $79, tertiary students $99, and an acute appointment for a sudden problem — a red eye, a foreign body, a sudden change in vision — is $69. Where further testing is needed it is quoted before it is done: visual fields $69, macular OCT $69, full OCT $194, anterior segment OCT $39, corneal topography $59, optical biometry $49, cycloplegic refraction $59. Specialist appointments are priced separately. A keratoconus consultation is $139 for 30 minutes or $169 for 45. An ortho-k consultation is $129. A full dry eye evaluation, which produces a written treatment plan, is $247 — it assumes a current full eye examination, either with us ($129) or a full examination record from another practice within the last six months. Fees elsewhere in New Zealand vary widely, and a lower advertised price usually means a shorter appointment with imaging charged as an extra or not offered at all. It is worth comparing what is included rather than the headline number. Ring us on 07 847 3195 if you want the fee for your situation confirmed before you book.
No practice can honestly claim that, and you should be wary of any that does — "best" depends entirely on what your eyes need. If your eyes are straightforward, several good practices in Hamilton will look after you well, and we would rather say that than pretend otherwise. What separates practices is what they can measure, and what they can treat when things are not straightforward. Rose was built around the complicated end. The Rose K lens for keratoconus was designed in this practice, and lenses of that family are, on the manufacturer's figures, among the most widely prescribed in the world for the irregular cornea. We hold swept-source OCT, corneal tomography, epithelial thickness mapping, two independent optical biometers for monitoring a child's short-sightedness, and objective tear film assessment. For dry eye we hold intense regulated pulsed light, LipiFlow, Blephasteam, Tixel and Rexon-Eye — to the best of our knowledge no other practice in New Zealand has all of these under one roof. A better question than "who is best" is "who is set up for what I have". Ask any practice you are considering how long the appointment is, what they can measure, and whether imaging is included or extra. Those answers will tell you more than a ranking would.
Not usually as a full examination, but there are genuinely free and subsidised pathways worth knowing about. Pre-school children are screened free through the B4 School Check, and there is vision screening in schools. Both are screenings rather than eye examinations — they are designed to catch obvious reduced vision and they miss a great deal, including focusing problems and early short-sightedness. A child who passes a screening can still need glasses. Children under 16 whose family holds a Community Services Card, or who hold a current High Use Health Card, may be eligible for the government spectacle subsidy towards an examination and glasses. MSD criteria apply, and we accept MSD and WINZ payment cards. Southern Cross members can use their optical benefits with us, and we offer Afterpay, Genoapay, QCard and GoCardless. We also run two free 15-minute chats. The myopia chat is for parents of a short-sighted child who want the options explained and want help deciding what is actually right for their family, with our experience behind that decision rather than a brochure. The ortho-k chat is for anyone considering overnight lenses who wants to understand what is involved before committing. Neither is an eye examination, but both are a proper conversation with someone who does this work. If cost is the reason you have been putting off having your eyes checked, ring us on 07 847 3195 and say so. We would rather find a way than have you not come.
While payment is generally required on the day of appointment, we do offer a number of payment options including Afterpay, Genoapay, QCard, and GoCardless.
Yes, we do.
Yes, you can.
Yes, if you are under 16 years of age you may be eligible for a subsidy for glasses. MSD criteria apply.
No. We are closed on public holidays and long weekends as we believe our staff should have the chance to enjoy this time with friends and family.
If your eyes are straightforward, almost any good optometrist can look after you well, and we would rather say that than pretend otherwise. Come to us when something is not straightforward: a prescription that will not settle, a cornea that has changed shape, a child whose short-sightedness is moving faster than it should, an eye surface that has stopped being comfortable, or a diagnosis you have been given but do not understand. Those problems are decided by measurement, and measuring them properly needs instruments most practices do not have.
Yes, and you do not need to justify it. A second opinion is not a criticism of whoever saw you first — very often they were right, and what you actually needed was the finding explained and the numbers put in front of you. What we can add is measurement. We can image the layers of your cornea and retina, map the epithelium, quantify how far your cornea sits from normal, measure the length of your eye and check your tear film objectively. That turns “something is not right” into a number, and a number either explains the problem or rules it out. Bring any previous scans, prescriptions and letters. Comparison against your own past results is often the most valuable thing in the room.
Usually. Complex is what this practice was built around — keratoconus, corneal grafts, irregular corneas after surgery or injury, severe dry eye, high prescriptions, and eyes that have been told they are not fittable with contact lenses. The Rose K lens for keratoconus was designed in this practice, and lenses of that family are, on the manufacturer's figures, among the most widely prescribed in the world for the irregular cornea. If we cannot help, we will tell you at the first appointment and tell you who can, rather than taking you through a course of treatment that was never going to work.
Not necessarily. “Not fittable” usually means not fittable with the lens designs and the measurements available at the time. Corneal mapping, epithelial thickness imaging and modern scleral and custom lens designs have moved a long way, and eyes that were genuinely unfittable ten years ago are often routine now. What we can promise is an honest answer after we have measured, not before.
Measure things that are usually not measured. Swept-source OCT of the cornea gives us tomography, full-thickness mapping, epithelial thickness mapping and an objective ectasia risk score. Retinal OCT with autofluorescence shows cellular-level change without any dye being injected. Optical biometry measures the length of the eye to a hundredth of a millimetre, which is how myopia is properly monitored. Objective tear film assessment and osmolarity replace guessing about dry eye. Most of these produce a baseline you can be compared against for the rest of your life, and that comparison is frequently worth more than any single result.
No. Anyone can book directly. Many of our patients are referred by their own optometrist, their GP or an ophthalmologist, and just as many simply ring us. A referral letter is useful because it saves repeating history, but it is not a requirement and it is not a condition of being seen.
No, and we would not build a referral practice on that basis. We accept referrals every week from optometrists across the Waikato and well beyond — Specsavers, OPSM, Bailey Nelson, Visique, For Eyes and independent practices alike. The patient comes to us for the part that needs our instruments or our lens work, and goes back to you with a written plan and the imaging. We are also glad to talk a case through before you refer, and if you have an OCT but no biometer we can help you get objective myopia measures out of the instrument you already own. Please contact us for co-management.
Waiting is the one thing that cannot be undone. Short-sightedness is axial — the eye is physically growing too long — and that length does not come back. What treatment does is slow the rate of growth, so the earlier it starts the more length is saved. We measure axial length directly on two independent biometers and plot it against normal growth curves, which means we can see a child drifting off their expected curve before the prescription changes. There is a free 15-minute myopia chat if you want to understand the options before committing to anything. It is worth being precise about what we are all trying to achieve. Myopia control does not stop a child's eyes changing and no practice should tell a parent it will. What it does, reliably and across many published trials, is slow the rate at which the eye lengthens — and because the risk of retinal detachment, myopic maculopathy and glaucoma in later life rises with every extra millimetre, slowing that growth is how a child is kept out of the range where sight is genuinely at risk. After seventeen years of focusing on this, we are now seeing children on customised plans whose axial length is not progressing at all over a monitoring period, and in some cases measurements that come back slightly shorter than the ones before them. That is our own clinical observation in our own patients rather than a trial result, and it has to be read carefully, because the choroid thickens when treatment is working and part of an apparent reduction can be that thickening rather than the eye itself shortening. That is precisely why we measure both. We are not yet able to tell a parent that we can stop myopia in its tracks, and we will not say it until we can.
Two things: we measure it before treating it, and we hold every current treatment technology in one building. Most dry eye is treated on the basis of symptoms, which is why drops so often fail. A tear film can be failing because the oil layer is blocked, because the water layer is short, because the surface is inflamed, or because the lids are the problem, and those need different treatments. We assess the tear film objectively with TearCheck — tear film stability, the oil layer, lid and gland imaging, and an inflammation measure — and measure tear osmolarity, the saltiness of the tears, which is the closest thing to a laboratory number for dry eye. Then we treat the cause. Rose holds intense regulated pulsed light for inflammation and gland function, LipiFlow thermal pulsation to clear blocked meibomian glands from the inner lid surface, Blephasteam controlled-humidity warming, Tixel thermomechanical treatment for the lids, and Rexon-Eye quantum molecular resonance for the more severe and treatment-resistant cases. At the time of writing, and to the best of our knowledge, no other optometrist or ophthalmologist in New Zealand has all of these available under one roof. We say that as a statement of fact rather than a boast, and we would be glad for it to stop being true. Dry eye is one of the most common and most under-treated conditions we see, and there are far more people living with it than one practice can look after. Any practice wanting to build this kind of service has our encouragement and our help — please contact us for co-management, and send us the cases you are not yet set up for. Why holding all of them matters is simple. A practice with one dry eye machine will offer you that machine. Holding all of them means the assessment decides the treatment, rather than the equipment deciding it — and when the first approach does not work, the next one is in the next room rather than in another city.
Yes — from around six weeks of age. Babies and toddlers are tested with Cardiff acuity cards and retinoscopy, neither of which needs the child to read a letter, name a picture or say a word. Most of the findings that matter in a young child cause no symptoms and are invisible to a parent, which is exactly why they need looking for.
There is one good reason: a baseline. Almost everything we look for — glaucoma, macular change, a cornea beginning to alter shape, an eye that is lengthening — is diagnosed by comparison over time rather than by a single reading. A scan taken while everything is normal is the reference every future scan is measured against, and it is the one you cannot go back and take later.
Because measurement takes time and we would rather not split it across visits. A first appointment usually involves imaging as well as examination, and you should expect to have the results shown to you and explained rather than summarised. If a problem is genuinely straightforward we will say so and keep it short.
In NZ an optometrist can calculate the prescription for glasses, fit contact lenses, diagnose and treat eye conditions and infections with medication. They can also manage ocular injuries including removing foreign objects. If surgery or specialist treatment is required they can refer to an ophthalmologist (eye surgeon), hospital, or other health care specialist. NZ-trained optometrists must complete a 5-year degree at the University of Auckland before becoming registered.
A dispensing optician has formal training in optical dispensing. They are qualified to help a client choose frames, read a prescription, discuss lens options, take measurements, order and fit glasses.
An ophthalmologist is a medical doctor who has specialised in the treatment of serious eye disease and ocular surgery such as cataract removal. They do not typically prescribe glasses or contact lenses.
Not always, and the difference is usually time and instruments rather than the optometrist. A low advertised fee generally buys a shorter appointment aimed at producing a spectacle prescription. That is a legitimate service and for many people it is enough. What it often does not include is retinal imaging, OCT scanning of the optic nerve and macula, measurement of eye length, or objective assessment of the tear film — the tests that find glaucoma before you notice it, detect macular change early, monitor a child's short-sightedness properly, or explain why your eyes feel gritty. At Rose a new patient appointment is 45 minutes, and imaging and the full pre-examination workup sit inside the $129 rather than on top of it. We are not the cheapest and do not try to be. Whichever practice you choose, three questions are worth asking: how long is the appointment, is imaging included or charged separately, and what happens to the images afterwards. A scan that is taken and kept becomes the baseline every future scan is compared against, and that comparison is frequently worth more than any single result.
Start with an optometrist in almost every case. An optometrist is your first point of contact for eye health and vision — examining the eyes, prescribing glasses and contact lenses, diagnosing eye disease, and in New Zealand treating many conditions with prescription medicines. An ophthalmologist is a medical doctor and eye surgeon who treats serious disease and performs surgery such as cataract removal, and who does not usually prescribe glasses or contact lenses. Neither is better than the other; they do different jobs. Most eye problems are diagnosed and managed by an optometrist, and where surgery or specialist medical treatment is needed we refer you promptly and stay involved in your care. The exception is anything sudden and severe: sudden loss of vision, a curtain across your vision, severe eye pain with a red eye, or a shower of new floaters and flashes. Phone us on 07 847 3195 rather than booking online — a person, not a calendar, decides how quickly you are seen — or go to hospital.
We are at 38 Lake Road in Frankton, with parking on site, a few minutes from the city centre and straightforward to reach from the western side of Hamilton. Our patients come from right across the city — Frankton, Dinsdale, Nawton, Te Rapa, Glenview, Hamilton East, Hillcrest, Chartwell, Rototuna and the central city — and from across the wider Waikato, including Cambridge, Te Awamutu, Morrinsville, Matamata, Huntly, Ngaruawahia, Otorohanga and Raglan. Because much of what we do is specialist work, a good number travel considerably further. We regularly see patients from Auckland, Tauranga, Rotorua, Taupo, Taranaki and the lower North Island for keratoconus, scleral and custom contact lens fitting, and complex dry eye — and we see patients from overseas who combine treatment with a trip. If you are travelling a distance, tell us when you book and we will group your appointments so the journey is worth making.
Forty-five minutes for a new patient, and the appointment is built so the measuring is done before you sit down with the optometrist. A full pre-examination workup and imaging are included in the fee rather than charged on top: assessment of your vision and prescription, examination of the front and back of the eye, eye pressure, and retinal imaging that becomes your permanent baseline. You will leave knowing what we found, what it means, and what — if anything — needs doing. If the honest answer is that nothing needs doing, that is what you will hear. If something needs watching or treating, you get a clear plan and a review date. Where a specific problem needs a specific test — visual fields, OCT, corneal topography, eye length measurement — those are quoted to you before they are done, never added afterwards without your agreement. Existing patients returning for a routine examination are booked for 30 minutes. Please arrive ten minutes early, and bring your current glasses or contact lenses, any recent prescription or referral letter, and a note of the medications you take, because some affect the eyes.
See things the Rose way
Make an appointment at Hamilton’s leading eye care specialists.

